Infant Journal
 Browse articles
LISA: does mild sedation increase the risk of intervention due to loss of respiratory drive? A systematic review
Less invasive surfactant administration (LISA) has become the preferred way to administer surfactant to neonates. However, discussion is still ongoing on whether sedation is required, particularly to preterm neonates. This paper is a review of the literature and evidence on sedation versus non-sedation for LISA.
Robyn Victoria Jones
MSc University of Southampton, Faculty of Health Sciences
robyn.jones5@nhs.net
Sarah Irwin
Clinical Teaching Fellow, University of Southampton
Jones R.V., Irwin S. LISA: does mild sedation increase the risk of intervention due to loss of respiratory drive? A systematic review. Infant 2024; 20(3): 124-28.
In the past, infants with respiratory distress syndrome (RDS) were mechanically ventilated (MV) and administered surfactant via endotracheal tube.1 However, it has been shown that prolonged periods of MV or positive pressure ventilation (PPV) in neonates increases risk of bronchopulmonary dysplasia, pneumothorax and intraventricular haemorrhage (IVH), especially in the preterm infant.2,3 Following Verder et al’s4 introduction of a “less invasive” technique to administer surfactant called INSURE in the 1990s,5 an even less invasive technique was introduced, known as less invasive or minimally invasive surfactant administration (LISA).6,7 During LISA, the spontaneously breathing infant on non-invasive respiratory support is delivered surfactant via a thin catheter passed through the vocal cords. It works to reduce the need for intubation and ventilation.7,8
LISA involves use of a laryngoscope to place the catheter between the vocal cords. Previous neonatal studies have determined that awake laryngoscopy is distressing and painful. Therefore, sedation is often used to comfort the patient during the procedure. Sedation is also used to reduce adverse events associated with pain, such as raised intercranial pressure, which can lead to IVH.9,10 However, it is also evidenced that with sedation, apnoea and bradycardia can result and lead to requirement for invasive ventilation, thus defeating the purpose.
Before LISA is carried out, clinical condition, gestation and age in hours will be considered.10,12
This systematic review will analyse the literature and evidence surrounding LISA for the preterm infant, with or without sedation.
Methods
Search strategies
The PICO (Population, Intervention, Comparator and Outcomes) tool was used to identify components of clinical evidence for this systematic review. PICO is also recommended by the Cochrane Collaboration of Systematic Reviews.13
Nine electronic databases, including the Cochrane Library, Medline, EMBASE, CINAHL, PUBMED, Academic Search Index, Science Citation Index, clinicaltrials.gov and Google Scholar were searched from the year 2012 up until 20th September 2022.
The first search strategy was (“Neonates requiring LISA” OR Neonates OR Respiratory distress OR RDS OR Neonate* OR NICU OR neonatal intensive care unit OR newborn OR intensive care Preterm infants OR Premat* OR newborn OR baby OR babies OR Respiratory distress syndrome OR RDS OR surfactant OR Less invasive surfactant OR LISA) AND (Sedation OR Intravenous fentanyl OR IV fentanyl OR Intravenous propofol OR IV propofol OR intravenous morphine OR IV morphine OR sedation OR analgesia OR pre medication) AND (Non-sedation, comfort care) The papers found from Search A were initially examined. However, there were a large number of records, so the terms (Apnoea* OR loss of respiratory drive OR Intervention Or Intubation OR Failure OR Bradycardia) were searched secondly then added to the first search with the Boolean operator AND to get the final results from the data base search.
A search was carried out on the National Institute for Health and Care Excellence (NICE) 202214 and the British Association of Perinatal Medicine (BAPM) 2021 websites.15 Reference lists of all key papers were also manually searched.
Eligibility criteria
This systematic review included all quantitative studies. Qualitative articles were excluded as data are immeasurable. Only peer-reviewed studies published in English were included, with a date restriction of 2012-2022. Only infants under 37 weeks’ gestation who required LISA within the first 72 hours of life were included.
Study selection
Of 119 articles identified, only 15 were eligible after title and abstracts were analysed and duplicates removed. Of these 15 papers, only eight studies were included after the inclusion/exclusion criteria had been applied. All of the studies used the quantitative research paradigm and were evaluated using the CASP checklist.16
Analysis
Design of studies
The majority of studies identified were cohort studies, four being prospective11,19,21,22 and two retrospective.17,18 Only two studies were randomised controlled trials (RCTs).20,23
Study population statistics and sample size
The number of infants included in the studies ranged from 29 to 495. Only two studies used a population of over 100.21,22 All were receiving some form of non-invasive respiratory support with an oxygen requirement as part of their inclusion criteria.11,17-23 All those included were classed as preterm with the gestational age ranging from 24+0 to 36+6 weeks, giving a median gestational age of 30+5 weeks. Nevertheless, only one study observed infants over 34+0 weeks gestation17 thus giving a two week upper age limit that would affect confidence intervals. If infants over 34+0 weeks were excluded, the mean gestational age would become 29+0 weeks, which is important to consider as analgesics/sedatives prior to LISA can increase the rate of apnoea and decreased blood oxygenation, especially in the preterm infant.5 In view of the wide gestational age, the range of weights was also considerably varied from 635-2,350g, giving an overall mean weight of 1,493g. This is also important to consider, as drugs like fentanyl, that rapidly distribute into muscle, remain in the plasma compart-ment for longer if the percentage of fat and muscle mass is lower.24 Both these factors are more pronounced in the premature neonate.25
Outcomes measured
All of the studies in this review11,17-23 measure the incidence of intubation during LISA, however, only four of them11,18,19,22 considered this as the primary outcome. Vital parameters during LISA were only measured as secondary outcomes in seven out of the eight studies.11,17-21,23 Pain scores were measured in four studies17,19,20,23 as primary outcomes, two of these were RCTs.18,23 Only two studies19,23 considered mortality rates. The incidence of IVH, NEC, PDA were measured in five studies,19,23 with four of these19,22 including the incidence of retino-pathy of prematurity (ROP) and four studies18,21 including the incidence of pul-monary haemorrhage and pneumothorax.
Sedation vs non-sedation in LISA
Three studies used ketamine as their sedation drug.18,19,22 Two used propofol17,20 and one used fentanyl.23 The large multicentre study21 used a combination of medications including ketamine, propofol, fentanyl, midazolam, phenobarbital, sufentanil and thiopental, depending on the unit and its protocol. The volume of sedation administered also varied, with dosage depending on level of activity. Four studies compared use of sedation with a control group that did not receive sedation.17,20,21,23 Three of the studies did not have a control group, observing LISA under sedation only.18,19,22 The remaining study observed LISA under no sedation.11 Ketamine was the preferred method of sedation used in three studies.18,19,22 It has rapid onset and peak effect, followed by a relatively short duration of action. However, it is also known as a potent anaesthetic that has received minimal study in neonates.25 Propofol was used in two studies.17,20 It has a rapid onset and recovery.26 Propofol is known to affect blood pressure.25-27 One study used fentanyl, which again has a rapid onset and shorter duration of action. However, clearance is substantially prolonged in the preterm or critically ill neonate.27 One study21 used mixed sedation methods, including propofol and ketamine, with ketamine being the main sedative. Despite extensive research, the optimal approach to assessment, nonpharmacologic care, and pharmacotherapy remains vague in the neonatal setting.28 The remaining study11 did not use any sedation for LISA. However, they did use nonpharmacological methods of analgesia such as swaddling, containment holding or sucrose. Only two of the other studies17,11,23 mention that they used nonpharmacological methods of analgesia. Evidence suggests nonpharmacological methods are effective and easily applied.29
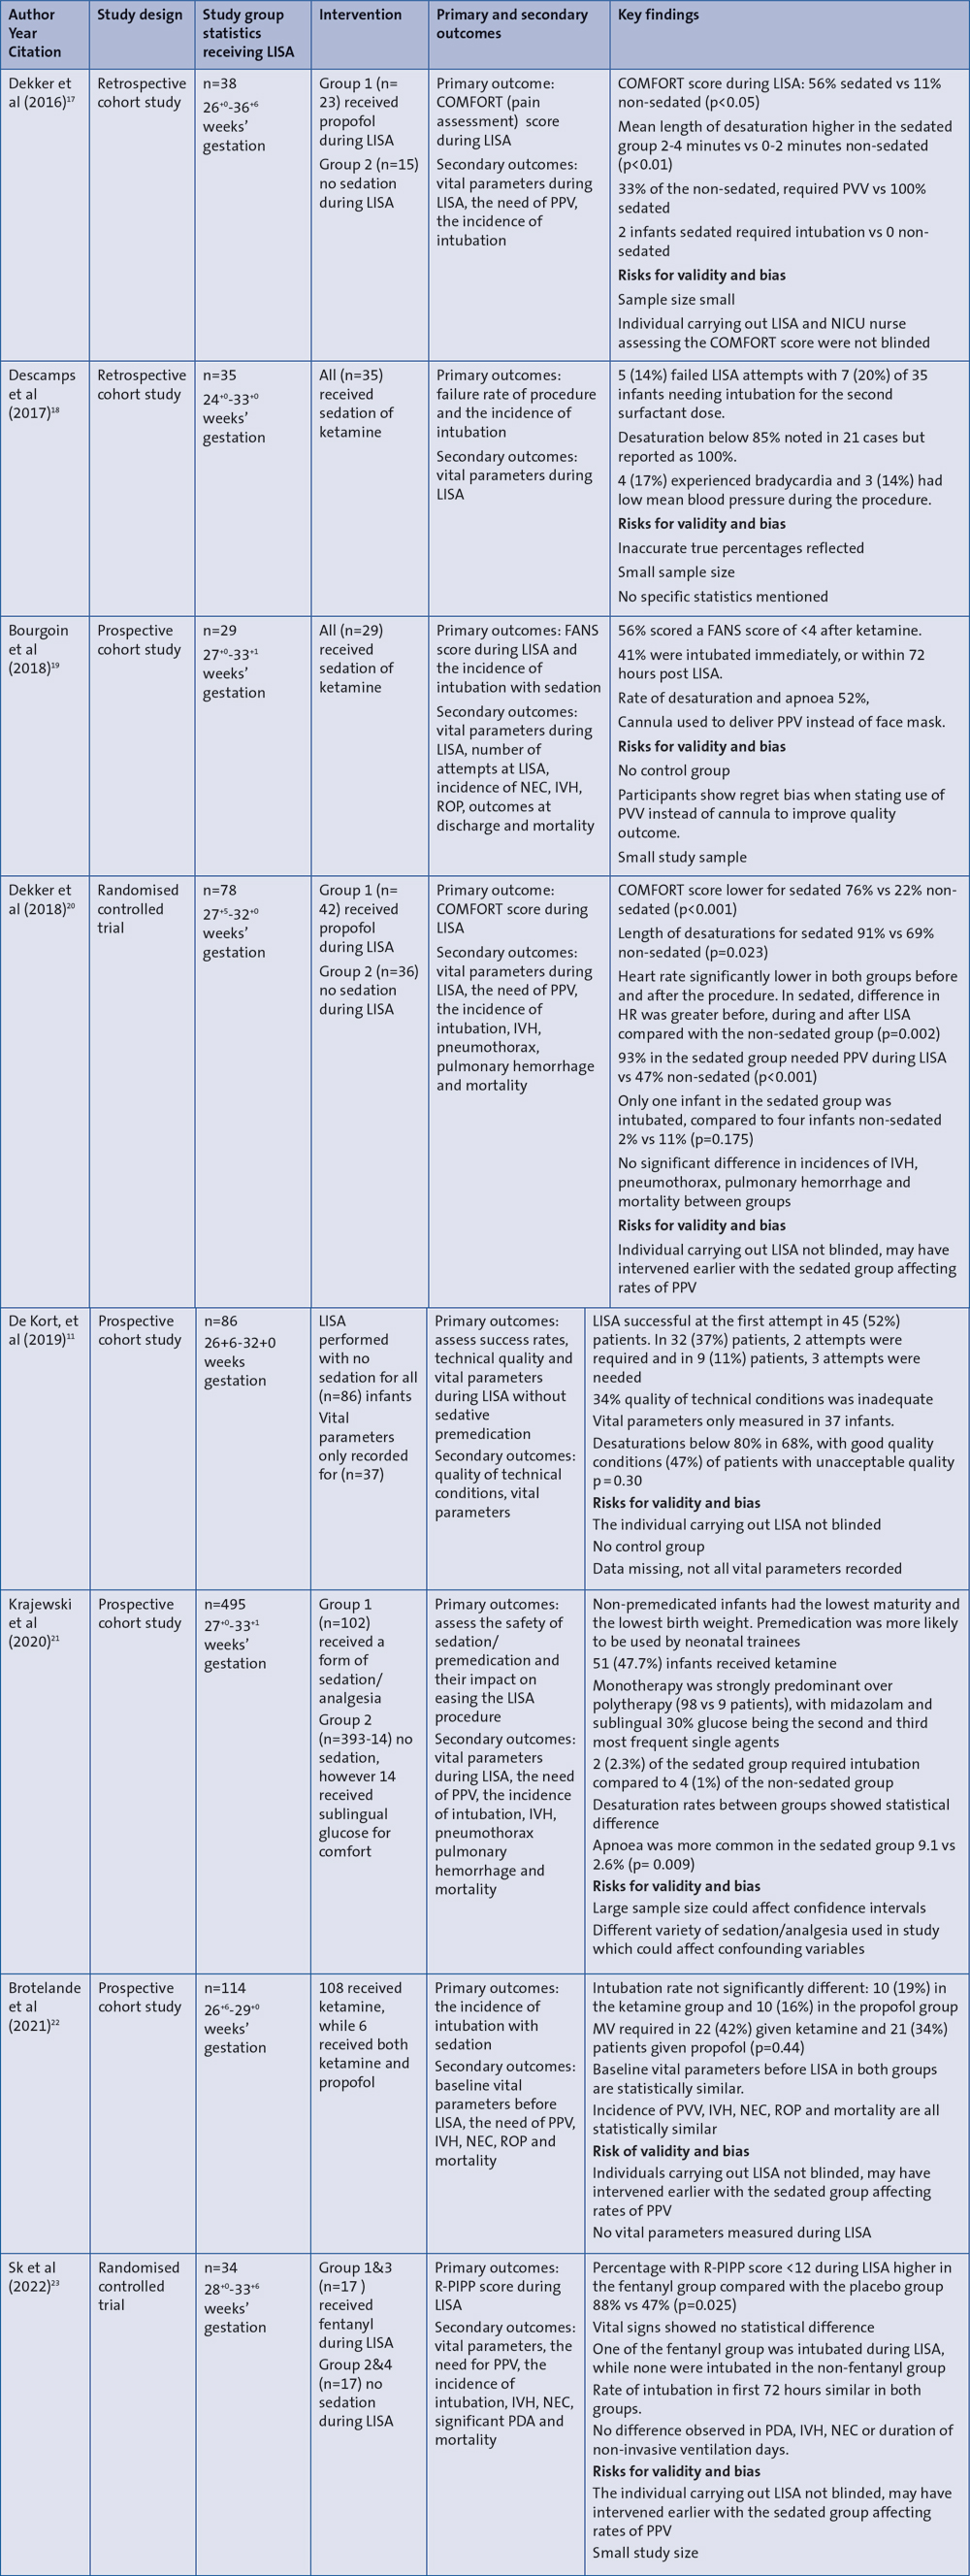
TABLE 1 Key: FANS=Faceless Acute Neonatal Pain Score; NEC=necrotising enterocolitis; IVH=intraventricular haemorrhage; ROP=retinopathy of prematurity; PPV=positive pressure ventilation; R-PIPP=revised premature infant pain profile.
Discussion
This literature review was conducted to determine whether use of sedation during LISA increases the risk of intervention and intubation due to apnoea and loss of respiratory drive. Dekker et al’s RCT17 was the first to be conducted on the use of sedation with LISA and was carried out in view of their previous retrospective study two years prior. Results show that more infants required intubation in the non-sedated group compared to sedated. However, it also showed that more infants in the sedated group needed intervention with PPV compared to the non-sedated group.
Although a single RCT is unlikely to prove causality, randomisation reduces bias and provides a rigorous tool to examine cause-effect relationships between intervention and outcome.30,31 However, the results of this and Sk et al’s23 RCT may not be a reliable source, as the primary outcomes for both studies assessed COMFORT score and not rate of intervention or intubation during LISA. In Sk et al’s RCT, only one of the fentanyl group was intubated during LISA, while none of the infants were intubated in the non-fentanyl group. The rate of intubation within the first 72 hours was similar in both groups and no data were provided as to whether PPV was used.
The rates of intubation being required following LISA with the two prospective studies only using sedation were similar. Bronte et al’s22 intubation rates were not significantly different between the ketamine and propofol group and MV was required by 38% in the overall study, but no data regarding PPV rates were given.
In Bourgoin et al’s19 study, 41% of infants were intubated immediately, or within 72 hours post LISA. In Decamps et al18 retrospective study, which used ketamine on all subjects, only 20% of infants needed intubation within the first hour. However, there are no data on rate of intubation after one hour or the incidence of PPV. Dekker et al’s17 retrospective study noted that 33% of the non-sedated group required PVV compared to 100% in the sedated group due to apnoea and desaturation; 5% in the sedation group required intubation. No infants in the non-sedated group required intubation.
Krajewski et al’s21 large prospective study showed 2.3% of the sedated group required intubation compared to 1% of the non-sedated group. De Kort et al’s11 non sedation approach study noted that LISA was successful in all infants. However, there are missing data and no further information to inform whether any of the subjects required intubation after the procedure.
The results of this systematic review show that intubation rates are not particularly different between groups. However, results do show the likelihood of infants requiring intervention with PPV is significantly higher in sedated infants. Nevertheless, the majority of the studies analysed were retrospective17,18 and prospective11,19,21,22 cohort studies. There are limitations with cohort studies as there is no randomisation to the subgroups of interest, hence cause and effect relationships cannot be determined, and relationships between variables must be stated as associations that may or may not be influenced by confounding factors.32,33
Conclusion
After extensively examining all of the literature, there is no evidence to support whether to give or withold sedation in the preterm neonate requiring LISA.
It is difficult to provide strong, conclusive, evidence-based recommen-dations as to which gestation a neonate requires premedication, and the risks associated with and without sedation during LISA.
Additional studies are needed to look at this question specifically, ensuring more RCTs with a wider sample size and adequate blinding that will impact and guide future practice.
 Free download PDF
Or read this article in our
Tablet/iPad edition
- There are no current guidelines on the use of sedation for LISA. As a result of sedation, preterm infants could become apnoeic, bradycardic, and may consequently require positive pressure ventilation.
- Preterm infants administered sedation who become apnoeic, may require intubation and mechanical ventilation.
Also published in Infant: